Diagnosis → Ophthalmology
Iridocyclitis
Inflammation of the anterior chamber involving the iris and ciliary body.
Also known as: AAU, Acute anterior uveitis, Anterior cyclitis, Anterior uveitis, Iritis
Etiology
Cause [nce][tdb][fvd]
Noninfectious (immune-mediated HLA-B27–associated)
Arthritis
Axial spondyloarthritis/ankylosing spondylitis
Psoriatic arthritis
IBD-associated arthritis
Reactive arthritis
Juvenile idiopathic arthritis
Multiple Sclerosis
Sarcoidosis
Behçet disease
Idiopathic
Infectious
Herpes simplex virus (HSV)
Varicella-zoster virus (VZV)
Cytomegalovirus (CMV)
Tuberculosis
Syphilis
Lyme disease
Drugs: Immune checkpoint inhibitor–associated anterior uveitis
Malignancy: Masquerade syndromes like lymphoma, leukemia, malignant melanoma
Pathophysiology [nce][fvd][qho]
Trigger and loss of ocular immune privilege
Infection
Autoimmunity
Immune-modulating drugs disrupt ocular immune privilege mechanisms (e.g., local immunosuppressive milieu in aqueous humor)
Breakdown of the blood–aqueous barrier
Increased vascular permeability in iris/ciliary body → protein exudation and leukocyte trafficking
Anterior chamber inflammatory cascade
Inflammatory cells/protein in aqueous humor → pain, photophobia, redness, hypopyon
Structural sequelae from ongoing/recurrent/chronic inflammation
Synechiae
Cataract
Secondary glaucoma/ocular hypertension
Macular edema
Risk factors [nce][tdb][fvd]
HLA-B27 positivity
Spondyloarthritis/IBD/psoriatic disease/reactive arthritis
Juvenile idiopathic arthritis
Smoking
Immune checkpoint inhibitors
Higher infectious exposure burden (TB, syphilis and Lyme in endemic regions)
Complications [nce][fvd]
Corneal scar
Non-resolving hypopyon
Synechiae
Macular edema
Cataract
Glaucoma
Iris atrophy
Optic nerve damage / optic disc swelling
Vitreous hemorrhage
Retinal detachment
Vision loss
Occlusio pupillae
Festooned pupil
Seclusio pupillae
Endophthalmitis
Strabismus
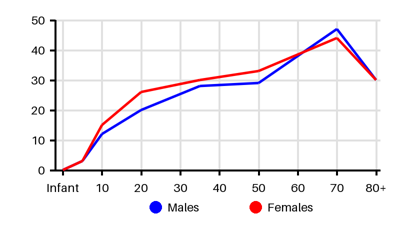
Epidemiology
Incidence per 100.000 [6sm][9vk]
Default
Symptoms & findings
Symptoms
Blurred vision, Keratic precipitates, Lacrimation, Miosis, Photophobia, Red eye, Synechia, Vitreous opacities
Clinical findings
ANA, Elevated CRP, Elevated Sedimentation Rate, HLA-B27, Hypopyon
Anamneses
None listed.
Localized findings
Approach
Approach [nce][tdb][fvd]
Confirm anterior uveitis on slit lamp:
Anterior chamber cells and flare
Keratic precipitates
Hypopyon
Synechiae
No primary corneal abrasion/keratitis or posterior uveitis
Intraocular pressure
Dilated fundus exam
OCT (optical coherence tomography) macula scan
Infectious exclusion often prioritized: syphilis, TB; Lyme in endemic areas
Consider sarcoidosis evaluation: Chest imaging ± ACE
Anterior Chamber Tap for aqueous PCR if suspecting viral anterior uveitis
Syphilis Serology
HIV Serology
HLA-B27 screening
Treatment
Topical corticosteroid: Prednisolone 1% (taper over weeks guided by AC cells) [nce]
Cycloplegic Atropine 1%: Dilate the pupil, pain control, prevent/break synechiae
Intraocular pressure management
Refractory or high-risk disease: if inadequate control with topical therapy
Periocular/intraocular corticosteroid if complications
Systemic corticosteroids or vitreous implants for severe, bilateral, recurrent, or posterior spillover disease
Steroid-sparing systemic immunomodulatory therapy
HLA-B27–associated (SpA-associated)
If frequent recurrences/severe disease --> biologic DMARDs (anti-TNF, IL-6)
Viral anterior uveitis (HSV/VZV/CMV)
Add systemic antiviral therapy
Immune checkpoint inhibitor–associated anterior uveitis
Severe cases may require systemic corticosteroids and prompt discontinuing ICI per oncology guidance
Methotrexate can be considered if poor response to systemic steroids
Differential diagnoses
Conjunctivitis, Corneal abrasion, Corneal ulcer, Endophthalmitis, Episcleritis, Foreign body, Glaucoma, Keratitis, Lymphoma, Retinitis, Scleritis, Subconjunctival hemorrhage, Trauma
References
[1] Gurnani B, Kim J, Tripathy K, et al. Iritis. [Updated 2023 Aug 25]. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2026 Jan-. Available from: https://www.ncbi.nlm.nih.gov/books/NBK430909/
[2] Chang EL, et al. Consensus disease definitions for ophthalmic immune-related adverse events of immune checkpoint inhibitors. J Immunother Cancer. 2025.
[3] Maghsoudlou P, Epps SJ, Guly CM, Dick AD. Uveitis in Adults. JAMA. 2025. . 11.3 Gelfman S, et al. A large meta-analysis identifies genes associated with anterior uveitis. Nat Commun. 2023.
[4] Pan S, et al. Beyond the joints: mechanistic insights and multidisciplinary strategies for spondyloarthritis-associated uveitis. Front Immunol. 2025.
[5] Xu, T. T., Reynolds, M. M., Hodge, D., & Smith, W. (2021). Epidemiology of Uveitis in Olmsted County, Minnesota: A Population-Based Follow-Up Study. Ocular immunology and inflammation, 31, 112 - 118.
[6] Acharya NR, Tham VM, Esterberg E, et al. Incidence and Prevalence of Uveitis: Results From the Pacific Ocular Inflammation Study. JAMA Ophthalmol. 2013;131(11):1405–1412.